


Contents
Scroll to:
https://doi.org/10.37489/2588-0519-GCP-0031
EDN: GRRZAK
Scroll to:
Background. Bacterial infections are an important cause of morbidity and mortality in children of different age groups, and Gram-positive flora plays an important role in the development of infections of various localization. Linezolid is one of the main antibiotics used to treat these diseases. It`s pharmacokinetics in children have a number of features that need to be considered in order to optimize therapy to ensure its maximum effectiveness and safety. This is very important for newborn population, and especially for premature infants.
Objective. Search, review, analysis and generalization of the results of pharmacokinetic and pharmacodynamic (PK/PD) studies of linezolid in children of different age groups.
Materials and methods. The information was searched in the scientific electronic library eLIBRARY.ru and the PubMed database for combinations of keywords: «дети или новорождённые» и «линезолид» и «фармакокинетика или фармакокинетический (ая) или ФК/ФД или популяционный (ая) или модельный (ая) или терапевтический лекарственный мониторинг или ТЛМ», as well as «(infant OR newborn OR neonate OR pediatric) AND (linezolid) AND (pharmacokinetic OR PK/PD model (ling) OR population model (ling) OR therapeutic drug monitoring OR TDM» for the period from 01.01.2000 to 31.12.2025. At the initial screening stage, articles describing linezolid pharmacokinetic studies in the pediatric patient population in the treatment of bacterial infections were selected by title and annotation, and at the next stage, full-text identification of selected articles was performed. The analysis did not include studies that lacked the necessary details. Systematic reviews, as well as case reports and studies based on the analysis of adult patient data, were excluded from further consideration.
Results. The studies included into the analysis demonstrated heterogeneous results regarding PK parameter distributions, significant covariates of the PK parameters, optimized dosing regimens to maximize the probability of attaining the desired PK/PD targets. This was most likely due to the high PK variability of linezolid in pediatric populations, as well as the small and heterogeneous patient samples in these studies.
Conclusion. The identified pediatric population PK/PD studies have shown that the pharmacokinetics of linezolid is age-related, and in different age groups is characterized by significant interindividual variability, therefore, standard doses, even taking into account covariates, are not optimal for all patients. Optimization of dosage in the pediatric patient population is possible based on the therapeutic drug monitoring procedure and Bayesian PK/PD modeling.
Zyryanov S.K., Bondareva I.B., Putsman G.A. Pharmacokinetics and pharmacodynamics of linezolid treatment of bacterial infections in children of different age groups: what do we know today? Kachestvennaya Klinicheskaya Praktika = Good Clinical Practice. 2026;(2):113-129. (In Russ.) https://doi.org/10.37489/2588-0519-GCP-0031. EDN: GRRZAK
Child mortality has been and remains one of the most important problems of global healthcare [1, 2], being a significant characteristic of the demographic situation in a country, demonstrating the features of the national healthcare system [3].
The causes of mortality in children of different age groups vary; nevertheless, there is a common feature in the mortality structure—infectious diseases are always present, although their share may vary. In particular, in the structure of infant mortality, endogenous causes—i.e., conditions arising in the perinatal period (81.8%) and congenital anomalies—come first. The leading components of these conditions are hemorrhagic disorders in the newborn (19.8%), respiratory distress syndrome (16.1%) and bacterial sepsis (12.8%). In older children, exogenous causes—injuries, poisonings and external causes—are in first place, but infectious and parasitic diseases, as well as respiratory diseases, play an important role [3].
It is also necessary to note a special group of concern for neonatologists and pediatricians worldwide—premature newborns. Infectious diseases and complications play an important role in the mortality structure of this group of patients—in particular, according to WHO data in 2010, 64% of deaths of children under 5 years of age worldwide were caused by infectious diseases [4, 5, 6]. In Russia, respiratory diseases, especially pneumonia, ranked second among causes of death in children under 1 year of age (82.7 per 100,000 live births), second only to congenital anomalies [7]. Bacterial sepsis in newborns also plays an important role—39.4‰ [8, 9].
Currently, the proportion of the premature newborn population is gradually increasing, due to the overall increase in the availability of medical care, as well as the improvement and development of modern medical technologies for nursing newborns. In addition, the concept of "late childbirth" leads to an increase in the proportion of women with chronic pathology [10, 11].
In the structure of primary outpatient morbidity of children aged 0–14 years, respiratory diseases occupy leading positions, with pneumonia (74.3%) playing the leading role in the structure of these diseases [12]. In the pathogen structure, Streptococcus pneumoniae (41.2–94%) plays a leading role [12–14], and over the years there has been an increase in the resistance of pneumococcal strains to penicillins, macrolides and other antibacterial drugs, which requires the use of reserve drugs.
Sepsis is the main nosocomial cause of mortality in children of all ages. The highest incidence is characteristic of intensive care units, since it is in these departments that the most invasive procedures (mechanical ventilation, catheterization) are performed, which are always associated with a high risk of nosocomial flora acquisition and the development of bacterial infections [15–20]. Depending on the localization, the etiological structure of sepsis may vary; nevertheless, Gram‑positive flora predominates in the development of sepsis due to nosocomial pneumonia, skin and soft tissue infections, and bloodstream infections (Staphylococcus spp. and Streptococcus spp.) [21–23].
Also, Gram‑positive microflora occupies an important place in the structure of infections detected in premature newborns. Gram‑positive pathogens are the main causative agents of sepsis, both with early onset (EOS) and late onset (LOS) (according to various sources, from 33.2% in EOS to 71.6% in LOS). The most common are:
Staphylococcus spp. (6.3–77.0%) [20, 24–27], especially methicillin‑resistant Staphylococcus aureus (MRSA) (6.3–20.9%) [20], and coagulase‑negative staphylococci (CoNS) (up to 29.3%) [20, 24–27]. They are most often the causative agents of pneumonia—26–30% [28, 29], as well as meningitis—26.0–28.5% [30, 31].
Streptococcus spp. (8.4–18.8%), in particular group B streptococci (8.4–18.8%) [25, 26]. They are most often the etiological factor in the development of meningitis (up to 50%) [32, 33], as well as pneumonia, but to a lesser extent—9–13% [28, 29].
Enterococcus spp. (5.3–9.5%) [20, 24–26]. They play an important role in the development of pneumonia (19–33%) [28, 34], as well as urinary tract infections (10–19.6%) [35–38].
For the eradication of the identified pathogens, it is extremely important to choose the optimal antibacterial drug and an adequate dosing regimen. For successful elimination of the pathogen, it is necessary to take into account the peculiarities of pharmacokinetics (PK) and pharmacodynamics (PD) in children, and this is even more important to consider when treating newborns and premature newborns. Unsatisfactory outcomes of infectious diseases can often be explained by incorrect selection of the dosing regimen of an antibacterial drug (ABP), which does not allow achieving the plasma and infection site concentrations necessary for eradication of the pathogen [39, 40], or more precisely, the target values of PK/PD indices (parameters) reflecting the pharmacological activity of the ABP.
Due to the growing resistance of pathogens to traditional antibiotics such as ampicillin, aminoglycosides and cefotaxime, adequate therapy often requires glycopeptides, for example vancomycin, but its use is limited by high nephrotoxicity [41–47].
One of the most widely used narrow‑spectrum ABPs with high activity against the main representatives of Gram‑positive microflora, in particular against staphylococci, is linezolid. According to generally accepted recommendations, the dosing regimen for children under 12 years of age is 10 mg/kg every 8 hours, for adolescents 12–17 years old — 600 mg twice daily, as in adult patients. In premature newborns (gestational age (GA) <34 weeks and postnatal age (PNA) <8 days), due to pharmacokinetic features, longer intervals between administrations may be recommended than in older children—up to 12 hours [48].
However, the literature contains studies in which, in adult patients receiving standard dosing regimens, according to therapeutic drug monitoring (TDM) data, almost half of the patients had linezolid concentrations outside the recommended range, while more than 30% of patients had a risk of concentration‑dependent hematological adverse events due to excess exposure, and this risk was especially pronounced in patients with reduced renal function [49, 50]. In special patient populations, including children and newborns, this percentage was even higher, leading to an increased risk of both underdosing and overdosing. All this indicates the importance of optimizing linezolid therapy taking into account pharmacokinetics and pharmacodynamics.
Linezolid therapy may be associated with adverse events: gastrointestinal symptoms (nausea, diarrhea, vomiting), hematotoxicity (myelosuppression), and lactic acidosis [51–56]. For linezolid, a strong association between exposure and efficacy, as well as some types of toxicity, is known, which also supports the optimization of linezolid dosing based on population PK/PD modeling.
During the period of linezolid use in clinical practice, population pharmacokinetics of linezolid in children has been studied in several studies, mainly in mixed age populations [57, 58]. At the same time, an extremely limited number of PK/PD studies of linezolid have been conducted in the newborn population, and even fewer in the premature newborn population.
The aim of our study was to search, review, analyze and summarize the results of conducted PK/PD studies of linezolid in children of different age groups.
Search methodology: systematic review, carried out in accordance with the requirements of the PRISMA guideline for systematic reviews and meta‑analyses. After selection of studies, the titles of articles were exported into a Microsoft Office (USA) 2019 spreadsheet: Microsoft Excel. After data analysis, tables were created in Microsoft Office (USA) 2019: Microsoft Word. Quantitative data were analyzed using arithmetic means, medians, minimum and maximum values (min‑max), and standard deviation. Qualitative data were described using absolute and relative values (%).
Databases searched: scientific electronic library eLIBRARY.ru, PubMed database.
Search period: from 01.01.2000 to 31.12.2025.
Keyword search: information was searched in the scientific electronic library eLIBRARY.ru and the PubMed database using combinations of keywords: «дети или новорождённые» и «линезолид» и «фармакокинетика или фармакокинетический (ая) или ФК/ФД или популяционный (ая) или модельный (ая) или терапевтический лекарственный мониторинг или ТЛМ», as well as «(infant OR newborn OR neonate OR pediatric) AND (linezolid) AND (pharmacokinetic OR PK/PD model (ling) OR population model (ling) OR therapeutic drug monitoring OR TDM».
Inclusion criteria:
Study population: pediatric (premature and term newborns, as well as children under 18 years of age);
Investigational drug: linezolid;
Studies involving the use of linezolid in patients with various bacterial infections;
Studies containing original PK studies of linezolid;
The concentration sampling scheme, dosing regimens, demographic and clinical characteristics of patients had to be described in detail;
The methods used for interpreting TDM data, pharmacokinetic, pharmacodynamic and/or population PK/PD modeling also had to be described in detail;
Years of publication: 2000–2025.
Studies were excluded if:
They were single case reports or review articles;
Studies describing the same population model;
Studies lacking data on linezolid PK parameters;
Articles including tuberculosis therapy;
The work did not present demographic and anthropometric data of the studied patient population;
Works included data from adult patient populations;
Studies were written in a language other than Russian or English.
Ethical approval. For this systematic review, ethical approval is not required.
Study identification. The PRISMA flow diagram is presented in Figure 1.
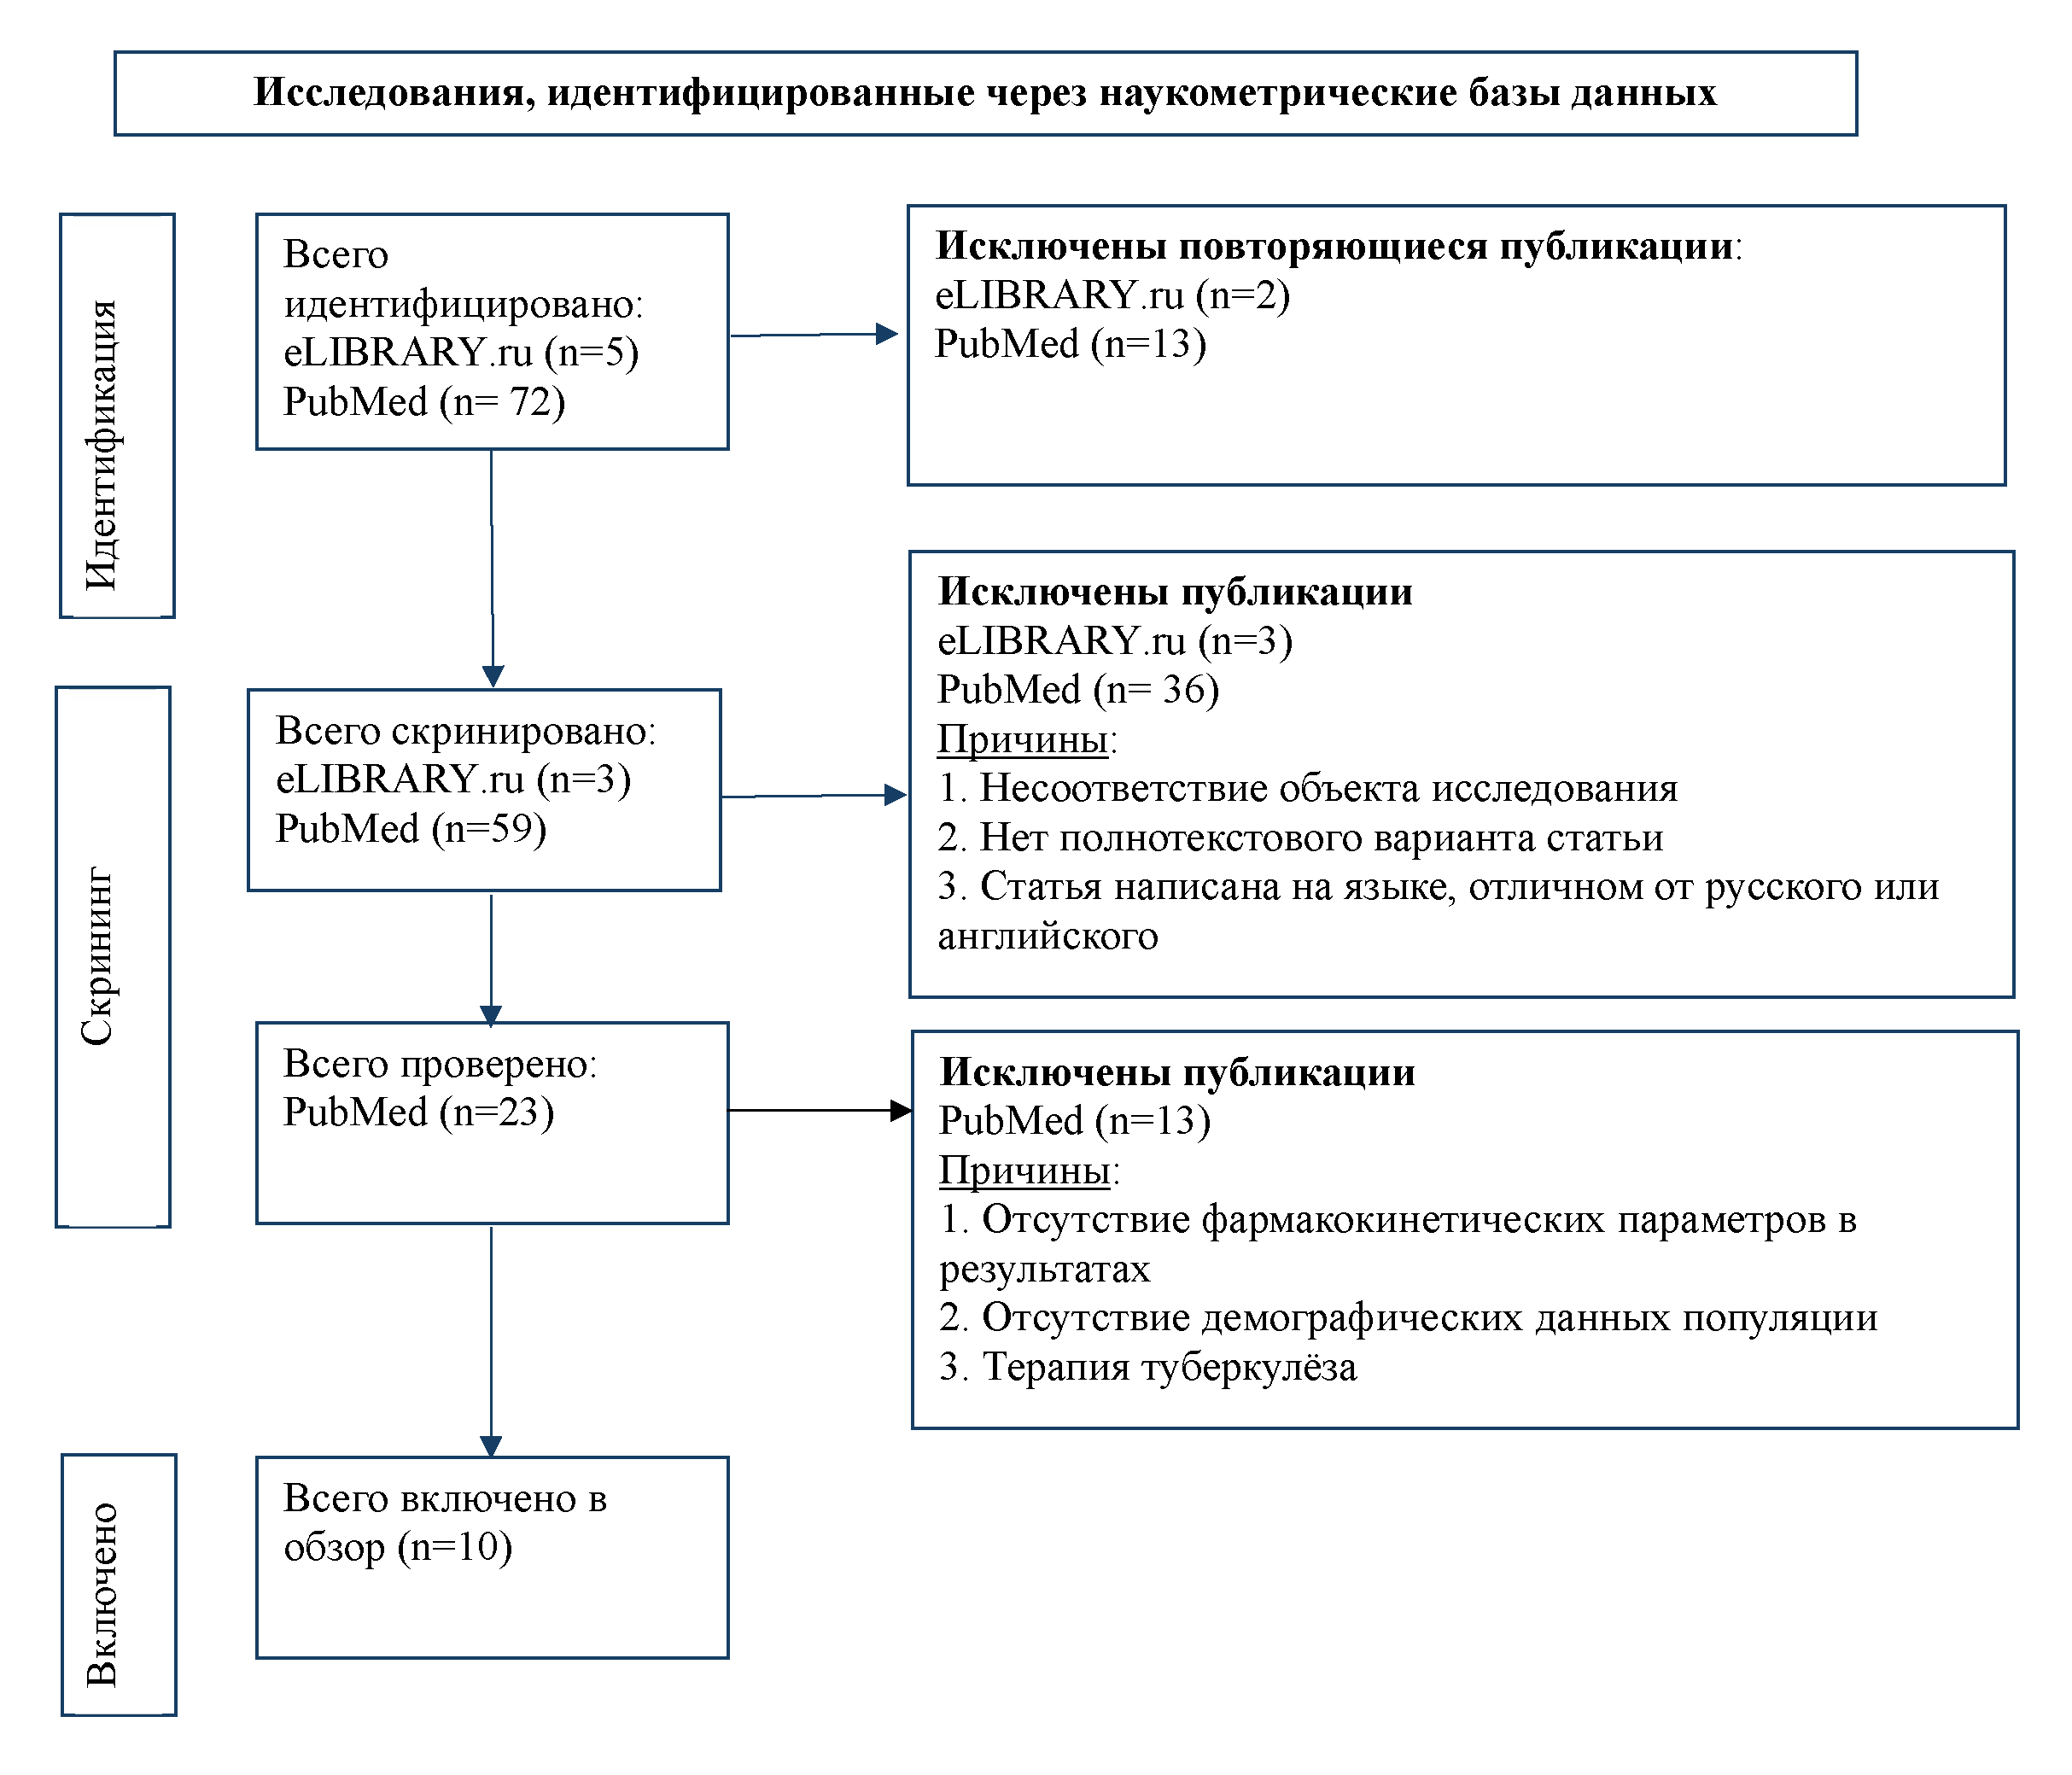
Figure 1. PRISMA Flow Diagram
Information on the main studies in this category is presented in Table 1. In the earliest PK study, 42 newborns were included and divided into 4 groups, depending on postnatal age (PNA, <8 days vs 8 days – 12 weeks) and gestational age (GA, <34 weeks vs ≥34 weeks). Sixteen patients had GA <34 weeks. The study revealed that in all patients with different GA and PNA ≤3 months, after a single intravenous dose of linezolid 10 mg/kg, pharmacokinetics varied significantly during the first week of life depending on PNA [59]. It was shown that linezolid clearance in newborns with PNA <7 days was on average lower than in newborns with longer PNA. At the same time, in premature newborns (GA <34 weeks) during the first week of life, clearance was lower than in the other patients. Clearance increased significantly during the first week of life, regardless of GA, so that in newborns with PNA >7 days it was on average 3 times higher than in adults [59, 60].
In a retrospective study by Sicard et al., PK data from 16 premature newborns (24 linezolid concentrations) were studied, with a mean PNA at the start of therapy of 3 weeks; 12 patients had GA less than 28 weeks. Patients received linezolid intravenously as a prolonged intravenous infusion and orally: a dose of 10 mg/kg every 8 hours for oral administration or 30 mg/kg for intravenous infusion. This work can be considered the first PK/PD study of linezolid in premature newborns based on TDM data, although without calculation of a population model and PK parameters. The main limitations of this study were the small sample size and intravenous/oral dosing of linezolid, as well as the absence of quantitative estimates of PK parameters and their variability [61].
In the PK/PD study by Thibault et al. in premature newborns, data from 26 patients (78 linezolid concentrations: median 3 (1‑7) per patient) were retrospectively studied, and a one‑compartment PK model was developed [55]. The median (min‑max) values of PNA, GA and body weight in the patients included in the study were 24 days (8‑88), 27 weeks (25‑36) and 1423 g (810‑3256), respectively. Twenty‑three patients (88%) had GA <34. The median value of the linezolid doses received was 10 mg/kg (8.1‑15) every 8 hours in 18 newborns (69%) or every 12 hours in 1 patient (4%). Seven patients (27%) received linezolid both every 8 h and every 12 h due to dose interval adjustment during TDM. The median duration of therapy was 13 days (2‑45). Samples for linezolid concentration measurement during the TDM procedure were taken at least after 48 hours of therapy at three time points: before the next dose, 0.5 h and 2‑3 h after the end of infusion. PK data were analyzed based on population modeling (a one‑compartment PK model adequately described the data). The final population PK model of linezolid included PNA and body weight as significant covariates for clearance, and only body weight for volume of distribution. The effect of PNA likely reflects the maturation of hepatic and renal function, which is fundamentally important for linezolid pharmacokinetics. Estimates of population values of linezolid clearance (0.17±0.17 L/h/kg and 0.16±0.03 L/h/kg in newborns with GA <34 weeks and ≥34 weeks, respectively) [59]. It should be borne in mind that there were only 3 patients with GA ≥34 weeks in the study, so the results should be interpreted with caution. Kearns et al. did not include clinically unstable patients with organ dysfunction in their study [59], whereas such patients were included in the Thibault C. study, so the study may have included more severely ill patients. Hepatic dysfunction in severe illness may probably explain the lower clearance values, although no association was found between linezolid clearance and AST and ALT values, possibly due to the limited number of measurements of these laboratory parameters available for analysis. Another explanation for the difference in average parameter values may be that Kearns et al. studied linezolid PK after a single dose, whereas in the Thibault C. study linezolid pharmacokinetics was at steady state. The fact that linezolid clearance at steady state is somewhat lower than after a single dose in healthy volunteers has been previously described [55]. A hypothesis was put forward that linezolid may inhibit its own metabolism by inhibiting the mitochondrial respiratory chain, leading to a decrease in clearance over time [62]. The authors Thibault C. et al. suggested that the absence of concentration measurements in their work before reaching steady state may have prevented observation of this phenomenon. The volume of distribution was larger in patients with GA <34 weeks, as expected, due to differences in total body water and body weight in premature and extremely premature infants. Estimates of volume of distribution were at the upper limit of previously published values (0.99±0.17 L/kg and 0.72±0.03 L/kg versus 0.87±0.13 L/kg and 0.65±0.21 L/kg in patients with GA <34 weeks and 34 weeks, respectively) [59].
In a prospective PK/PD study of linezolid [63] in the premature newborn population, 54 patients (PNA = median 24 days (8‑88 days)) receiving the standard dosing regimen were included. Eighty‑four linezolid concentrations at steady state after 4 maintenance doses were measured: trough concentrations and concentrations within the dosing interval. Each patient had 1‑2 concentrations measured, at least one of which was a trough. The study used a one‑compartment PK model with first‑order linear elimination. Among covariates, body surface area (BSA) was selected as the most significant for clearance (CL) and volume of distribution (V). It was shown that in premature newborns, BSA may be considered the main covariate affecting the total clearance of linezolid, possibly due to the development of organs and systems, especially the kidneys [86].
| Dosing regimen | Number of patients, n | PNA, days | GA, weeks | Body weight, g | Median / mean duration of therapy, days | Linezolid clearance, L/h/kg | AUC0‑∞¹, mg*h/L | Source |
|---|---|---|---|---|---|---|---|---|
| 10 mg/kg single dose | 9 | <8 | <34 | 2780 (min — 740, max — 6200) | Not applicable | 0.12±0.06 (min 0.05 — max 0.24) | 108.1±50.59 (min 41.38 — max 190.7) | Kearns GL et al. [59] |
| 7 | ≥8 | <34 | 0.31±0.07 (min 0.23 — max 0.39) | 33.98±8.01 (min 25.78 — max 44.0) | ||||
| 11 | <8 | ≥34 | 0.23±0.12 (min 0.09 — max 0.53) | 53.41±25.19 (min 18.98 — max 102.54) | ||||
| 15 | ≥8 | ≥34 | 0.31±0.10 (min 0.20 — max 0.59) | 33.88±8.54 (min 16.89 — max 49.52) | ||||
| 42 | 0.25±0.12 (min 0.05 —max 0.59) | 54.92±39.33 (min 16.89 — max 190.7) | ||||||
| 10 mg/kg 3 times daily | 18 | 24 (min — 8, max — 88) | 27 (min — 25, max — 36) | 1423 (min — 810, max — 3256) | 13 (min — 2, max — 45) | 0.17±0.17 in patients with GA <34 weeks | AUC0‑24 184.6 (min 110.0 — max 393.5) | Thibault C et al. [55] |
| 0.16±0.03 in patients with GA >34 weeks | ||||||||
| 10 mg/kg 2 times daily | 1 | |||||||
| 10 mg/kg 3 times daily → 10 mg/kg 2 times daily | 7 | |||||||
| 10 mg/kg 3 times daily oral or 30 mg/kg/day — intravenous infusion | 12 | 20.9±11.7 | <28 wks | <1000–11 1001‑1500–4 1501‑2500–1 | 7.6±3.1 | No data | No data | Sicard M et al. [61] |
| 3 | 28‑32 | |||||||
| 1 | 32‑36 | |||||||
| 16 |
Note: ¹ AUC — area under the plasma concentration‑time pharmacokinetic curve.
The main studies in this category are presented in Table 2. A population PK/PD model of linezolid including children from 0 to 12 years (body weight from 2.1 to 46 kg) was presented in the work of Li et al. [64]. Of the 91 patients included in the study, 91 had normal renal function (GFR ≥90 mL/min1.73 m²), 17 patients had reduced renal function (GFR 60 — <90 mL/min1.73 m²), and 4 patients had moderate renal impairment (GFR 30 — <60 mL/min*1.73 m²). Patients received linezolid therapy for at least three days, the dosing regimen was a 1‑hour intravenous infusion of 10 mg/kg every 8 hours. A total of 135 linezolid concentrations were included in the PK analysis: 47 were trough concentrations, 5 were peak concentrations at 0.5 hours after the end of infusion, and the remaining 83 samples were taken at time points between Cmax and Ctrough. In this study, body weight and GFR were found to be significant covariates for linezolid clearance. The mean value of linezolid clearance in the study was estimated as 0.13 L/h/kg, which is consistent with estimates from another PK/PD study in children, which reported a mean clearance of 0.152 L/h/kg estimated in 14 patients aged 2 to 11 years [65].
In another PK/PD study [66], 15 patients aged 0‑13 years (3 patients with PNA ≤3 months) were included, receiving linezolid orally and/or via intravenous infusion, usually the prescribed dosing regimen was 10 mg/kg three times daily. All further dose adjustments were made according to the attending physician's decision. The analysis was based on 92 measurements of total linezolid concentration and 70 measurements of its free concentration. As in previous studies of linezolid pharmacokinetics in children, clearance depended on patient age, and PNA was a significant covariate. This is consistent with the results of Thibault et al. [55]. The authors [66] included PNA in the PK model in the form of a maturation function (Hill model). The estimated parameters of this model indicate that clearance significantly increases with increasing PNA, and the observed marked variability in CL values should be taken into account when dosing linezolid. Body weight was used in the model for allometric scaling of CL and V. The mean values for linezolid half‑life in the study in a patient with body weight 9.9 kg and age 24 months (median values in the study) were estimated as 3 hours. This value is not inconsistent with estimates from other pediatric PK studies of linezolid (1.8–2.9 h) [60, 64, 67]. The risk of linezolid‑associated thrombocytopenia (observed in three patients in the study) was estimated as 21.4%. In these patients, the mean trough concentration was 19.8 mg/L, significantly higher than in patients without: 6.84 mg/L. Therefore, dosing adjustments based on linezolid concentration measurements may be recommended to improve therapy safety. Although dose adjustments based on patient covariates—body weight and maturation (based on PNA)—were performed in the study, and cases of thrombocytopenia were observed and occurred at high trough linezolid concentrations, it can be concluded that dosing adjustment based on TDM may be recommended for optimizing linezolid therapy in children.
Only the free fraction of the drug produces clinical response and adverse effects, while it is extremely rare in PK studies of linezolid in children that free drug concentration in blood was measured. The final estimate of protein binding in the study [66] was estimated as 18.9%, and no significant interindividual variability in this parameter was observed in the study. The results obtained are consistent with the results of studies in adult patients [68, 69], and the authors conclude that there is no need to measure the free fraction of linezolid in clinical practice for routine TDM. Although this point needs further study, especially in patients with potential clinically significant changes in binding.
Another PK/PD model in children (63 patients) with severe infections in critical condition, aged 0.10‑15.30 years and body weight 4.2‑70.0 kg (of which 14 patients under 1 year of age) was presented in the article [70]. Linezolid was administered intravenously over 1‑2 hours at a dose of 10 mg/kg three times daily for patients <12 years and 600 mg twice daily for patients 12‑18 years. Four blood samples after reaching steady state were taken from each patient: trough and peak concentrations, as well as two samples at different intermediate time points. A two‑compartment model with first‑order linear elimination was used to describe the PK data. Body weight and AST were identified as significant covariates for clearance. In the study, patients with AST >40 U/L had much higher AUC values than patients with AST ≤40 U/L (205.45 vs 159.96, p <0.05). Interindividual variability for linezolid clearance was estimated as 52‑53%.
In the PK/PD study by Tian et al. [71], 80 patients were included, median age = 3.3 years (5‑95th percentile = 0.1‑12.6 years), and 157 linezolid concentrations after steady state (median = 2 measurements per patient) were used for PK/PD modeling. Linezolid therapy was administered via intravenous infusion at the standard dose of 10 mg/kg every 8 hours for children under 12 years and 600 mg every 12 hours for children 12 years and older. Based on a linear one‑compartment model, body weight and glomerular filtration rate (GFR) were considered statistically significant covariates for linezolid clearance. In this study, the median estimated GFR was 190.1 mL/min/1.73 m², i.e., most patients included in the study had augmented renal clearance (ARC, GFR >130 mL/min/1.73 m²). Total linezolid clearance values ranged from 0.13 to 0.171 L/h/kg, and apparent volume of distribution from 0.42 to 0.92 L/kg. Mean clearance and volume of distribution values of 0.15±0.06 L/h/kg and 0.77±0.50 L/kg, respectively, are consistent with the results of other PK/PD studies of linezolid in the pediatric population [64, 67].
In most PK/PD studies of linezolid in the pediatric patient population, the traditional linear one‑compartment model was used as the structural model. The choice of the simplest traditional PK model may be due to the fact that most of these studies used relatively sparse TDM measurements. The observed differences in estimates of population PK parameter values may largely be explained by differences in the studied patient populations, including differences in age, severity of illness, renal and hepatic function, as well as differences in the design of the studies themselves, including the concentration sampling scheme.
If we try to summarize the results presented in the literature, it can be said that the pharmacokinetics of linezolid in the pediatric population demonstrates age dependence. Thus, in children under 12 years of age, linezolid clearance is on average faster and half‑life is on average shorter compared to adult patients. Although in newborns in the first days after birth, linezolid clearance values are on average similar to those in adult patients, during the first week of life clearance increases fairly rapidly, and increases approximately 2‑3 times by the end of the first week. Subsequently, linezolid clearance decreases, reaching levels characteristic of adult patients in adolescents [72]. The authors of [66] showed that postnatal age is associated with linezolid clearance. This is consistent with the results of previous studies showing significant variability in linezolid pharmacokinetics during the first week of life. On average, linezolid clearance observed in 7‑day‑old infants was lower than in older children. Clearance continued to increase during the first 2‑3 months of life [60]. Consideration of the development of organs and systems in the pediatric patient population is very important for optimal dosing [72].
However, in the study on which the recommended dosing regimen for newborns was based [59], only 9 patients were premature newborns with GA <34 weeks and PNA <7 days. The linezolid dosing recommended in the package insert for newborns with PNA >7 days does not consider gestational age at all. Therefore, it can be said that the recommended dosing regimen does not take into account the peculiarities of linezolid pharmacokinetics and its age‑related changes in newborns depending on GA and PNA in patients older than 7 days. In children of different ages, physiological changes occur that can significantly affect pharmacokinetic processes in the body. This makes it practically impossible to extrapolate dosing regimens estimated for adult patients or for older children to younger children, and especially to newborn patients.
The authors of the study [73] for premature newborns, based on modeling, proposed the following dosing scheme based on patient BSA—a significant covariate for clearance and volume of distribution of linezolid in the study: 6 mg/kg every 8 hours for BSA = 0.11 m², 7 mg/kg every 8 hours for BSA = 0.13 m² and 9 mg/kg every 8 hours for BSA = 0.15 m² at MIC ≤1 mg/L; 7 mg/kg every 8 hours for BSA = 0.11 m², 8 mg/kg every 8 hours for BSA = 0.13 m² and 10 mg/kg every 8 hours for BSA = 0.15 m² at MIC = 2 mg/L.
In the works [73, 74], the estimated glomerular filtration rate (GFR) was considered a significant covariate for linezolid clearance. Linezolid clearance was higher in patients with augmented renal clearance (ARC) (GFR >130 mL/min/1.73m²) compared to patients with normal renal function (90 ≤ GFR ≤ 130 mL/min/1.73m²) in [74], which is similar to conclusions made for the adult population. In [73], it was shown that AST can be considered a covariate for total linezolid clearance, reflecting the role of hepatic metabolism in linezolid elimination. The authors proposed to consider AST level when choosing the linezolid dosing regimen: dose of 10 mg/kg every 12 hours for children under 12 years and 600 mg every 48 hours for children 12‑18 years with AST >200 U/L at MIC = 1 mg/L.
The contradictory results observed in population PK/PD studies of linezolid, including with regard to optimized dosing regimens, are likely related to the high variability of linezolid clearance in pediatric populations [57]. In addition, most of these studies are based on very small patient samples. This may also be the reason that in different studies, different covariates for the main PK parameters of linezolid turn out to be statistically significant and then participate in the development of optimal dosing regimens. The distributions of adverse events during linezolid therapy presented in the studies also differ, which may also be related to the small and heterogeneous patient samples in the conducted studies.
| Dosing regimen | Number of patients, n | Age, years | Body weight, kg | Linezolid clearance, L/h/kg | Cmin¹, mg/L | AUC0‑24, mg*h/L | Source |
|---|---|---|---|---|---|---|---|
| 10 mg/kg every 8 hours | 112 | 2.9±3.4 | 13.9±10.2 | 0.13 | No data | No data | Li et al. [64] |
| 10 mg/kg every 8 hours | 14 | 4.9±2.8 (2‑11 years) | 19.0±9.5 | 0.152±0.74 | 2.57 (min 1.33 — max 5.12) | 240.35 (min 174.04 — max 394.74) | Cojutti P et al. [65] |
| 600 mg every 12 hours | 9 | 14.9±1.3 (12‑18 years) | 57.2±18.5 | 0.067±0.04 | 2.90 (min 1.36 — max 4.16) | 298.68 (min 203.50 — max 654.97) | |
| 10 mg/kg every 8 hours | 15 | 0‑13 (3 patients with PNA <3 months) | 9.9±3.0 | 0.523 | No data | No data | Ogami C., et al. [66] |
| 10 mg/kg every 8 hours | 57 | 5.21±4.22 | 22.28±15.00 | 2.34 L/h | No data | No data | Yang M et al. [70] |
| 600 mg twice daily | 6 | ||||||
| 10 mg/kg every 8 hours | 80 | 3.3 (min 0.1 — max 12.6) | 12.5 (min 5.3 — max 45.9) | 0.13‑0.171 | Minimum value = 0.25 In 14.9% (10/67) patients, the safety limit for Cmin = 7 mg/L was exceeded | No data | Tian X et al. [71] |
| 600 mg twice daily | 5 | ||||||
| 120 mg 3 times daily | 3 | 12.3 | 0.646±0.239 | 3.4±1.6 | 175.1±41.6 | Matsumoto K et al. [67] | |
| 200 mg 3 times daily | 4; 6 | 19.0; 20.7 | |||||
| 220 mg 3 times daily | 8 | 22.3 | |||||
| 600 mg twice daily | 11 | 63.3 |
Note: ¹ Cmin — minimum (trough) concentration of the drug in blood plasma.
The antibacterial activity of linezolid can best be characterized by two PK/PD parameters: the area under the pharmacokinetic curve over 24 hours at steady state divided by the MIC (AUC0‑24/MIC), usually for optimizing efficacy in adult patients in the range ≥80‑120, and the percentage of time during the day that the drug concentration exceeds the MIC (%T>MIC), usually 85‑100% [75‑78].
Target ranges of PK/PD parameters for efficacy and safety of therapy in the pediatric population and the newborn population have not yet been strictly justified. In the work of Rao et al. [79], it was suggested that AUC0‑24/MIC values in the lower range for adult patients of 80‑100 may be used as a suitable target for linezolid therapy in children, since in children linezolid clearance is on average significantly faster than in adults. In [55], AUC0‑24/MIC >80 and AUC0‑24 <300 were chosen as target ranges for efficacy and safety in premature newborns, respectively. A large number of studies have reported a linear relationship between trough linezolid concentrations and AUC0‑24 [79]. Given the clinical and ethical difficulties of obtaining multiple blood samples for reliable estimation of AUC0‑24/MIC or %T>MIC, measurement of only trough concentration and interpretation taking into account MIC may be a practical indicator of therapeutic efficacy and safety of linezolid therapy. Measurement of trough concentrations is a fairly simple and frequently used method for monitoring linezolid toxicity. Various studies have proposed the following target ranges for trough concentrations: 2‑8 mg/L, 3.6‑8.2 mg/L or 2‑7 mg/L [79]. Experts recommended maintaining trough concentrations in the range of 2‑8 mg/L in both children and adult patients [63]. In the study [73], the following target ranges were used for modeling: 2‑8 mg/L for trough linezolid concentrations and 80‑300 mg*h/L for AUC0‑24.
In the PK/PD study by Tian et al. [71], the AUC0‑24/MIC ≥80 ratio was used as the main PK/PD index for efficacy, and the safety threshold was exceeding the trough concentration Cmin = 7 mg/L.
Target ranges of PK/PD parameters can be used within the framework of population modeling to evaluate the performance of ABP dosing regimens—the probability of target attainment (PTA) in patients of the studied population. Assuming a MIC level, the PTA can be estimated from data on patients receiving a particular dosing regimen or from simulation results (in the latter case, as the proportion of virtual "patients" for whom the target values of PK/PD indices were "attained" according to modeling results). At PTA ≥90%, the ABP dosing regimen can be considered acceptable.
In most of the reviewed PK/PD studies, patients received the recommended intravenous linezolid dosing regimen for the treatment of bacterial infections: a dose of 10 mg/kg three times daily for children under 12 years and 600 mg twice daily for children 12 years and older. In accordance with the recommendations, in the PK/PD study by Duan et al. [73] in the premature newborn population, patients received the dosing regimen: 10 mg/kg twice daily at GA <34 weeks and PNA <7 days, and 10 mg/kg three times daily at GA ≥34 weeks and at GA <34 weeks with PNA >7 days.
In the work of Li et al., for children from 0 to 12 years, based on the obtained PK parameter estimates, the risk of underdosing was assessed when receiving the linezolid dosing regimen of 10 mg/kg every 8 hours for the treatment of infections with MIC ≥2 mg/L. According to the study, when receiving this dosing regimen, only 81.70% and 35.81% of patients (PTA) achieved the recommended level of PK/PD parameter AUC0‑24/MIC ≥80 against pathogens with MIC = 2 mg/L and 4 mg/L, respectively, indicating the need for dose increase. The authors proposed to increase doses to 15‑20 mg/kg every 8 hours in this patient population at MIC ≥2 mg/L. The conclusion about the risk of suboptimal dosing based on the recommended linezolid dosing regimen is consistent with the results of another PK/PD study of linezolid in children [65]. In this study, a retrospective PK analysis of TDM data was performed, and it was shown that the recommended dosing was suboptimal (Cthrough below the recommended range) in half of patients aged 2 to 11 years, and that higher doses may be required in the presence of bacteria with MIC above 1 mg/L. Increasing the dose to 15 mg/kg every 8 hours may be required for MIC = 2 mg/L. For the recommended dosing regimen, PTA ≥90% for AUC/MIC >100 is achieved only at MIC ≤1 mg/L. None of the studied linezolid dosing regimens in the study guarantee an acceptable PTA at MIC = 4 mg/L.
The authors of [65] conclude that the use of TDM may help optimize linezolid dosing, especially for the treatment of infections caused by pathogens with intermediate susceptibility to linezolid and/or for patients receiving concomitant therapy with drugs such as proton pump inhibitors, dexamethasone, phenobarbital and amiodarone, which significantly affect linezolid plasma concentrations. TDM may also help avoid toxic linezolid concentration levels, which is especially important during long‑term therapy, and thus reduce the frequency of the most well‑known dose‑dependent hematological adverse event—thrombocytopenia.
The authors of [55] demonstrated that linezolid doses up to 12 mg/kg every 8 hours may be required in the premature newborn population to achieve PTA ≥90% at MIC = 2 mg/L.
In the study [70] in the pediatric population of critically ill patients, based on the PK parameter estimates obtained from PK/PD modeling, higher doses of up to 15 mg/kg every 6 h were calculated as optimal for pathogens with MIC = 2 mg/L to achieve the target AUC/MIC >80. No dosing regimen was proposed by the authors for MIC = 4 mg/L.
According to the results of [74], the standard dosing regimen in children does not require adjustment even for MIC = 2 mg/L. For children under 12 years, in the case of pathogens with MIC = 4 mg/L, only the dosing regimen of 600 mg every 12 hours can achieve an acceptable PTA of 90.5%. However, such a dose increase leads to an increased risk of exceeding the safety threshold (up to 48.6%). Therefore, in this case, to optimize linezolid therapy, an attempt should be made to achieve a balance between efficacy and safety. For children aged 12 years and older, in the case of MIC = 4 mg/L, for the standard dosing regimen of 600 mg every 12 hours, PTA = 0.0%. Increasing the dose to 900 mg every 12 hours or 600 mg every 8 hours allows achieving PTA = 83.3% at MIC = 4 with a low probability of exceeding the safety threshold (trough concentration = 7 mg/L).
Thus, it can be concluded that the dosing regimens considered optimal in different studies in the pediatric population differ somewhat due to differences between PK/PD studies, and external validation is required for each such regimen to recommend its use in real clinical practice, taking into account population characteristics.
The reviewed PK/PD studies of linezolid demonstrate that the pharmacokinetics of linezolid in all age groups of the pediatric population is characterized by significant interindividual variability; therefore, the standard dosing regimens developed based on these studies are not optimal for all patients [49, 80‑86]. In the presented population studies of linezolid in children, interindividual variability of PK parameters reached 53% for total clearance and 82% for apparent volume of distribution. Residual unexplained PK variability by the final population model was also considerable, reaching 60%.
Such pronounced variability creates a risk of both underdosing and overdosing when using standard regimens, even adjusted for covariates, in pediatric patients. The dosing regimens of linezolid proposed in different studies themselves differ due to differences between PK/PD studies and extremely limited sample sizes.
All this supports the personalization of linezolid dosing based on TDM data in the pediatric patient population. This is especially important for special patient groups, in particular newborns and premature newborns, as well as patients with impaired renal function, augmented renal clearance, hepatic dysfunction, critically ill patients, and in the case of suspected or estimated pathogen MIC values of 2 mg/L and above.
The use of software for the Bayesian approach and population modeling will allow individualization of therapy based on sparse TDM measurements from real clinical practice, start monitoring concentrations and adjusting therapy without waiting for steady state, as well as calculate PK/PD indices to assess target attainment based on TDM data. It should be noted that in domestic hospitals, TDM has not yet become a routine procedure, due to the difficulties of staff training, the high cost of equipment, and the lack of clear clinical guidelines. Nevertheless, large centers are gradually introducing TDM procedures into practice, which allows more effective and safe prescribing of therapy to patients in special age groups.
1. Dattani S, Spooner F, Ritchie H, et al. Child and Infant Mortality. Our World in Data. Available from: https://ourworldindata.org/child-mortality. [Accessed 20 January 2026]
2. From cradle to cane: WHO’s new European Health Report warns of lifelong health crises across the Region. Available from: https://www.who.int/europe/news/item/25-02-2025-from-cradle-to-cane--who-s-neweuropean-health-report-warns-of-lifelong-health-crises-across-the-region. [Accessed 20 January 2026]
3. Baranov AA, Albitskiy VYu, Namazova-Baranova LS. Child Mortality In Russia: Situation, Challenges and Prevention Aims. Voprosy sovremennoi pediatrii. 2020; 19 (2): 96-106. (In Russ.). doi:10.15690/vsp.v19i2.2102
4. Liu L, Johnson H, Cousens S, et al. Global, regional, and national causes of child mortality: an updated systematic analysis for 2010 with time trends since 2000. Lancet 2012; 379: 2151–61. doi:10.1016/S0140-6736(12)60560-1.
5. Howson CP, Kinney MV, Mcdougall L et al. Born Too Soon: Preterm birth matters. Reprod Health. 2013;10(S1):S1. doi:10.1186/1742-4755-10-s1-s1
6. Patel RM. Short- and Long-Term Outcomes for Extremely Preterm Infants. American Journal of Perinatology. 2016 Feb; 33 (3): 318-328. doi:10.1055/s-0035-1571202.
7. Sokolovskaya TA, Stupak VS, Menshikova LI, Postoev VA. Morbidity and causes of mortality among preterm and term newborns in the Russian Federation. Ekologiya cheloveka (Human Ecology). 2021; 28(5):20-28.
8. Sukhanova LP, Sklyar MS. Infant and perinatal mortality in Russia: tendensies, structure, risk factors. Social aspects of public health. 2007;4(4):2 (In Russ.)
9. Butranova OI, Ushkalova EA, Zyryanov SK et al. Developmental Pharmacokinetics of Antibiotics Used in Neonatal ICU: Focus on Preterm Infants. Biomedicines. 2023;11:940. DOI: 10.3390/biomedicines11030940.
10. Arkhangel'skiy VN, Kalachikova ON. Maternal age at fi rst birth: dynamics, regional differences, determination. Еconomic and social changes - facts trends forecast. 2020;13(5):200-217. (In Russ.). DOI: 10.15838/esc.2020.5.71.12.
11. Web Annexes. In: WHO recommendations for care of the preterm or low-birthweight infant. Geneva: World Health Organization; 2022. Available from: https://www.who.int/publications/i/item/9789240058262 [Accessed 15 December 2025]
12. Tsarkova SA, Kuznetsov PV, Kupreeva NG. Pneumonia in children: old challenges and new opportunities. Pediatric pharmacology. 2011;8(1):12-16 (In Russ.)
13. Chavanina SA, Bogomolova IK. Out-patient pneumonia in children: modern state of the problem. Zabaikalsky medical Bulletin. 2013;1:184-192. (In Russ.)
14. Katosova LK, Spichak TV, Kim SS et al. Etiological diagnostics of the acute pneumonia in children. Questions of diagnostic in pediatrics. 2009;2:27-31. (In Russ.)
15. Sheozheva AV, Sergevnin VI, Markovich NI. Endogenous and exogenous risk factors for infection of premature newborns with pathogens of purulent-septic infections. Perm Medical Journal. 2023;40(4):16-22. (In Russ.). DOI: 10.17816/pmj40416-22.
16. Volodin NN et al. Neonatology: National Guidelines. GEOTAR-Media, 2007. 848 p (In Russ.)
17. Cohen R, Romain O, Tauzin M, et al. Neonatal bacterial infections: Diagnosis, bacterial epidemiology and antibiotic treatment. Infectious Diseases Now. 2023 Nov; 53 (8S): 104793. doi:10.1016/j.idnow.2023.104793.
18. Cortese F, Scicchitano P, Gesualdo M, et al. Early and Late Infections in Newborns: Where Do We Stand? A Review. Pediatric Neonatology. 2016 Aug; 57 (4): 265-273. doi:10.1016/j.pedneo.2015.09.007.
19. Aranda JV, Cataldi L, Fanos V. Clinical pharmacology of antimicrobials for urinary tract infections in newborns and young infants. Journal of Chemotherapy. 2006 May; 14-15. doi:10.1080/1120009x.2006.11782421.
20. Flannery DD, Edwards EM, Coggins SA, et al. Late-Onset Sepsis Among Very Preterm Infants. Pediatrics. 2022 Dec 1;150(6):e2022058813. doi: 10.1542/peds.2022-058813.
21. Krasnov MV, Krasnov VM. Sepsis at children of early age: modern criteria of the diagnosis and principles of treatment. Practical medicine. 2010;1(40):28-39. (In Russ.).
22. Serhiyenka EN, Romanova ON. Microbiological characteristics of sepsis in children. Klinicheskaia infektologiia i parazitologiia. 2022;11(1):80-87. (In Russ.). doi:10.34883/PI.2022.11.1.026.
23. Khubieva ER, Khubieva DR. Sepsis in Children. Innovative Potential for the Development of Science in the Modern World: Achievements and Innovations: Collection of Scientifi c Articles Based on the Materials of the XIII International Scientifi c and Practical Conference, Ufa, December 12, 2023. Pp. 162-164. (In Russ.).
24. Grigorenko GV, Zabolotskikh TV, Serga AP et al. Features of the course of sepsis in newborn children. Issues of modern pediatrics. Особенности течения сепсиса у новорождённых детей. Вопросы современной педиатрии. 2006;5(1):162 (In Russ.).
25. Flannery DD, Edwards EM, Puopolo KM, et al. Early-Onset Sepsis Among Very Preterm Infants. Pediatrics. 2021 Oct; 148 (4). doi:10.1542/peds.2021-052456.
26. Vasilyev AY, Kalmykova AS, Obedin AN. Inflammation Markers in the Early Diagnosis of Neonatal Sepsis in Premature Infants. Modern Problems of Science and Education. 2021. No. 3. p. 128. (In Russ.). doi:10.17513/spno.30828.
27. Ivanov DO. Systemic inflammatory response in neonatal sepsis: is it the same? Translational Medicine. 2014;(1):53-61 (In Russ.). DOI:https://doi.org/10.18705/2311-4495-2014-0-1-53-61
28. Kushnareva MV, Keshishyan ES, Balashova ED. The etiology of neonatal pneumonia, complicated by bronchopulmonary dysplasia. Journal of Neonatal-Perinatal Medicine. 2019; 12 (4): 429-436. doi:10.3233/NPM-17159.
29. Volyanyuk EV, Safi na AI. Congenital Pneumonia in Premature Infants: Features of Etiology, Diagnosis, and Treatment. Practical Medicine. 2011;5(53):55-59 (In Russ.).
30. Shane AL, Hansen NI, Moallem M et al. Surgery-Associated Infections among Infants Born Extremely Preterm. The Journal of Pediatrics. 2022 Jan; 240: 58-65. doi:0.1016/j.jpeds.2021.08.064.
31. Shane AL, Hansen NI, Stoll BJ et al. Methicillin-resistant and susceptible Staphylococcus aureus bacteremia and meningitis in preterm infants. Pediatrics. 2012 Apr; 129 (4): e914-22. doi:10.1542/peds.2011-0966.
32. Baud O, Aujard Y. Neonatal bacterial meningitis. Handb Clin Neurol. 2013;112:1109-13. doi: 10.1016/B978-0-444-52910-7.00030-1.
33. Neonatal Bacterial Meningitis. Режим доступа: https://www.msdmanuals.com/professional/pediatrics/infections-in-neonates/neonatal-bacterial-meningitis.
34. Markhulia HM, Kushnareva MV, Dementieva GM [et al.]. Etiology of ventilator-associated pneumonia in premature newborns. Pediatrics named a Ther G.N. Speransky. 2005;84(3):36-39. (In Russ.).
35. Kushnareva MV, Dementyeva GM, Shabelnikova EI. Urinary Tract Infection in Premature Infants. Pediatrician's Practice. 2020;4:28-32 (In Russ.).
36. Petrova IV, Malyuzhinskaya NV, Khasieva II. Urinary tract infections in newborns. Fundamental and applied sciences today: Proceedings of the XIV International Scientific and Practical Conference, North Charleston, USA, February 20-21, 2018. Volume 2. – North Charleston, USA: CreateSpace, 2018. – pp. 41-44 (In Russ.).
37. Zhuravkova, AM. Etiology of urinary tract infection in newborns. Collection of materials of the Republican scientific and practical conference of students and young scientists dedicated to the 100th anniversary of the birth of Professor Vladimir Trofi movich Paramey, April 29-20, 2021 / Ministry of Health of the Republic of Belarus, Grodno State Medical University, Council of Young Scientists. – Grodno, 2021. – Pp. 212-213. (In Russ.).
38. Arshad M, Seed PC. Urinary tract infections in the infant. Clinics in perinatology. 2015 Mar; 42 (1): 17-28. doi:10.1016/j.clp.2014.10.003.
39. Dorofaeff T, Bandini RM, Lipman J et al. Uncertainty in Antibiotic Dosing in Critically Ill Neonate and Pediatric Patients: Can Microsampling Provide the Answers? Clinical the erapeutics. 2016 Sep; 38 (9): 1961-1975. doi:10.1016/j.clinthera.2016.07.093.
40. Simeoli R, Cairoli S, Decembrino N, et al. Use of Antibiotics in Preterm Newborns. Antibiotics (Basel). 2022 Aug 23; 11 (9): 1142. doi:10.3390/antibiotics11091142.
41. Filippone EJ, Kraft WK, Farber JL. The Nephrotoxicity of Vancomycin. Clinical Pharmacology and Therapeutics. 2017 Sep; 102 (3): 459-469. doi:10.1002/cpt.726.
42. Mergenhagen KA, Borton AR. Vancomycin nephrotoxicity: a review. Journal of Pharmacy Practice. 2014 Dec; 27 (6): 545-553. doi:10.1177/0897190014546114.
43. Rahmani H, Khalili H. Prevention of Vancomycin-Induced Nephrotoxicity; An Updated Review of Clinical and Preclinical Studies. Infectious Disorders - Drug Targets. 2022; 22 (2). doi:10.2174/1871526521666210331164552.
44. Stoma IO. Therapeutic drug monitoring of vancomycin in oncohaematological patients. Recept = Recipe. 2014;4:80-85 (In Russ.).
45. Sales GTM, Foresto RD. Drug-induced nephrotoxicity. Revista da Associaca o Medica Brasileira.(1992). 2020 Jan 13; 66 (Suppl. 1): s82-s90. doi:10.1590/1806-9282.66.S1.82.
46. Tantranont N, Luque Y, Hsiao M, et al. Vancomycin-Associated Tubular Casts and Vancomycin Nephrotoxicity. Kidney International Reports. 2021 May 12; 6 (7): 1912-1922. doi:10.1016/j.ekir.2021.04.035.
47. Shneider MM, Maschan AA, Rumyantsev AG. New Possibilities for the Treatment of Infections Caused by Gram-Positive Flora: Efficacy and Safety of Linezolid. Issues of Hematology/Oncology and Immunopathology in Pediatrics. 2003;2(4):87-91 (In Russ.)
48. State Register of Medicines: Linezolid. Available from: https://grls.minzdrav.gov.ru/Grls_View_v2.aspx?routingGuid=15e7490e-8f0e-4b87-91ab-775bfbecc0ec [Accessed 22 December 2025]
49. Cattaneo D, Gervasoni C et al. Therapeutic drug management of linezolid: a missed opportunity for clinicians? International Journal of Antimicrobial Agents. 2016 Dec;48(6):728-731. doi:10.1016/j.ijantimicag.2016.08.023.
50. Pea F, Cojutti PG, Baraldo M. A 10-year experience of therapeutic drug monitoring (TDM) of linezolid in a hospital-wide population of patients receiving conventional dosing: is there enough evidence for suggesting TDM in the majority of patients? Basic and Clinical Pharmacology and Toxicology. 2017;121(4):303–8
51. Ivzhits MA, Zyryanov SK, Ushkalova EA et al. The use of antibacterial drugs in premature newborns: experience in creating a formulary. Kachestvennaya Klinicheskaya Praktika = Good Clinical Practice. 2016;3:56-65 (In Russ.)
52. Kazanova AM, Ivzhits MA, Zyryanov SK. Modern Approaches to Improving the Effectiveness of Antimicrobial Therapy in Perinatology: Local Experience. Kachestvennaya Klinicheskaya Praktika = Good Clinical Practice. 2019;1:66-74. (In Russ.). DOI:10.24411/2588-0519-2019-10065.
53. Shneider MM, Maschan AA, Rumyantsev AG. New therapeutic possibilities for gram-positive infections: efficacy and safety of linezolid. Pediatric Hematology/Oncology and Immunopathology. 2003;2(4): 87-91.
54. Dekhnich AV, Khachatryan NN. New and Old Oxazolidinones. What Are the Differences Between Tedizolid and Linezolid? Clinical Microbiology and Antimicrobial Chemotherapy. 2017;19(2):121-129 (In Russ.)
55. Thibault C, Kassir N, Goyer I, et al. Population Pharmacokinetics of Intravenous Linezolid in Premature Infants. The Pediatric Infectious Disease Journal. 2019 Jan; 38 (1): 82-88. doi:10.1097/INF.0000000000002067.
56. Bayram N, Düzgöl M, Kara A et al. Linezolid-related adverse effects in clinical practice in children. Arch Argentinos de Pediatria. 2017 Oct 1; 115 (5): 470-475. doi:10.5546/aap.2017.eng.470.
57. Bandín-Vilar E, García-Quintanilla L et al. A review of population pharmacokinetic analyses of linezolid. Clinical Pharmacokinetics. 2022 Jun;61(6):789-817. doi:10.1007/s40262-022-01125-2.
58. Qin Y, Zhang LL, et al. Parametric population pharmacokinetics of linezolid: a systematic review. British Journal of Clinical Pharmacology. 2022 Sep;88(9):4043-4066. doi:10.1111/bcp.15368.
59. Kearns GL, Jungbluth GL et al. Impact of ontogeny on linezolid disposition in neonates and infants. Journal of Clinical Pharmacology and Therapeutics. 2003 Nov;74(5):413-22. doi:10.1016/S0009-9236(03)00226-1.
60. Jungbluth GL, Welshman IR et al. Linezolid pharmacokinetics in pediatric patients: an overview. the Pediatric Infectious Disease Journal. 2003 Sep;22(9 Suppl):S153-7. doi:10.1097/01.inf.0000086954.43010.63.
61. Sicard M, Launay E et al. Pharmacokinetics of linezolid treatment using intravenous and oral administrations in extremely premature infants. European Journal of Clinical Pharmacology. 2015 May;71(5):611-5. doi:10.1007/s00228-015-1813-3.
62. Stalker DJ, Jungbluth GL, et al. Pharmacokinetics and tolerance of single- and multiple-dose oral or intravenous linezolid, an oxazolidinone antibiotic, in healthy volunteers. Journal of Antimicrobial Chemotherapy. 2003 May;51(5):1239-46. doi:10.1093/jac/dkg180.
63. Lin B, Hu Y, et al. Expert consensus statement on therapeutic drug monitoring and individualization of linezolid. Front Public Health. 2022 Aug 10;10:967311. doi: 10.3389/fpubh.2022.967311.
64. Li SC, Ye Q, et al. Population pharmacokinetics and dosing optimization of linezolid in pediatric patients. Antimicrobial Agents and Chemotherapy. 2019 Mar 27;63(4):e02387-18. doi: 10.1128/AAC.02387-18.
65. Cojutti P, Maximova N, et al Pharmacokinetic/pharmacodynamic evaluation of linezolid in hospitalized paediatric patients: a step toward dose optimization by means of therapeutic drug monitoring and Monte Carlo simulation. Journal of Antimicrobial Chemotherapy. 2015 Jan; 70(1):198- 206. doi: 10.1093/jac/dku337.
66. Ogami C, Tsuji Y, To H, Yamamoto Y. Pharmacokinetics, toxicity and clinical effi cacy of linezolid in Japanese pediatric patients. J Infect Chemother. 2019 Dec;25(12):979-986. doi: 10.1016/j.jiac.2019.05.025.
67. Matsumoto K, Shigemi A, et al. Linezolid dosage in pediatric patients based on pharmacokinetics and pharmacodynamics. Journal of infection and chemotherapy. 2015 Jan;21(1):70-3. doi: 10.1016/j.jiac.2014. 08.017.
68. Tsuji Y, Holford NHG, et al. Population pharmacokinetics and pharmacodynamics of linezolid-induced thrombocytopenia in hospitalized patients. British Journal of Clinical Pharmacology. 2017 Aug;83(8):1758- 1772. doi:10.1111/bcp.13262.
69. Hashemian SMR, Farhadi T et al. Linezolid: a review of its properties, function, and use in critical care. Drug Design, Development and Therapy. 2018 Jun 18;12:1759-1767. doi: 10.2147/DDDT.S164515.
70. Yang M, Zhao L, Wang X, et al. Population Pharmacokinetics and Dosage Optimization of Linezolid in Critically Ill Pediatric Patients. Antimicrob Agents Chemother. 2023 May 1;95(5):e02504-20. doi: 10.1128/AAC.02504-20.
71. Tian X, Jiang T, Dong L, et al. Population pharmacokinetics and clinical assessment of linezolid in pediatric bacterial infections. Antimicrob Agents Chemother. 2025 May 7;69(5):e0129924. doi: 10.1128/aac.01299-24.
72. Gijsen M, Vlasselaers D et al. Pharmacokinetics of Antibiotics in Pediatric Intensive Care: Fostering Variability to Attain Precision Medicine. Antibiotics (Basel). 2021 Sep 28;10(10):1182. doi:10.3390/antibiotics10101182.
73. Duan L-f, Li J-j, et al. Th erapeutic drug monitoring of linezolid in Chinese premature neonates: a population pharmacokinetic analysis and dosage optimization. Antimicrobial Agents and Chemotherapy. 2024 Nov 6;68(11). doi:10.1128/aac.01148-24
74. Primasari FS, Hakim AR. Systematic Review of Linezolid Population Pharmacokinetics in Pediatric: Models, Covariates, and Dosing Implication. Journal of Management and Pharmacy Practice, Vol 15, No 4, 2025. Doi: 10.22146/jmpf.108892
75. Rayner CR, Forrest A et al. Clinical pharmacodynamics of linezolid in seriously ill patients treated in a compassionate use programme. Clinical Pharmacokinetics. 2003;42(15):1411-23. doi:10.2165/00003088-200342150-00007.
76. Abdul-Aziz MH, Alffenaar JC, et al. Antimicrobial therapeutic drug monitoring in critically ill adult patients: a Position Paper. Intensive Care Medicine. 2020 Jun;46(6):1127-1153. doi: 10.1007/s00134-020-06050-1.
77. Fujii M, Karumai T et al. Pharmacokinetic and pharmacodynamic considerations in antimicrobial therapy for sepsis. Expert Opinion on Drug Metabolism and Toxicology. 2020 May;16(5):415-430. doi:10.1080/1742 5255.2020.1750597.
78. Wang X, Wang Y et al Pharmacokinetics of Linezolid Dose Adjustment for Creatinine Clearance in Critically Ill Patients: A Multicenter, Prospective, Open-Label, Observational Study. Drug Design, Development and Therapy. 2021 May 19;15:2129-2141. doi: 10.2147/DDDT.S303497.
79. Rao GG, Konicki R et al. Th erapeutic Drug Monitoring Can Improve Linezolid Dosing Regimens in Current Clinical Practice: A Review of Linezolid Pharmacokinetics and Pharmacodynamics. Therapeutic Drug Monitoring. 2020 Feb;42(1):83-92. doi:10.1097/FTD.0000000000000710.
80. Pea F, Viale P, Cojutti P et al. Therapeutic drug monitoring may improve safety outcomes of long-term treatment with linezolid in adult patients. Journal of Antimicrobial Chemotherapy. 2012 Aug;67(8):2034-42. doi: 10.1093/jac/dks153.
81. Hui, L-A, Bodolea C et al. Linezolid Pharmacokinetics in Critically Ill Patients: Continuous Versus Intermittent Infusion. Antibiotics 2024, 13, 961. DOI: https://doi.org/10.3390/antibiotics13100961
82. Swoboda S, Ober MC, et al. Pharmacokinetics of linezolid in septic patients with and without extended dialysis. European Journal of Clinical Pharmacology. 2010 Mar;66(3):291-8. doi: 10.1007/s00228-009-0766-9.
83. Galar A, Valerio M, et al. Systematic Therapeutic Drug Monitoring for Linezolid: Variability and Clinical Impact. Antimicrobial Agents and Chemotherapy. 2017 Sep 22;61(10):e00687-17. doi: 10.1128/AAC.00687-17
84. Alsultan A. Determining therapeutic trough ranges for linezolid. Saudi Pharmaceutical Journal. 2019 Dec;27(8):1061-1063. doi: 10.1016/j.jsps.2019.09.002.
85. Morata L, De la Calle C et al. Risk factors associated with high linezolid trough plasma concentrations. Expert Opinion on Pharmacotherapy. 2016 Jun;17(9):1183-7. doi: 10.1080/14656566.2016.1182154.
86. Morata L, Cuesta M, et al. Risk factors for a low linezolid trough plasma concentration in acute infections. Antimicrobial Agents and Chemotherapy. 2013 Apr;57(4):1913-7. doi: 10.1128/AAC.01694-12.
Sergey K. Zyryanov — Dr. Sci. (Med.), Head of the Department of General and Clinical Pharmacology; chief non-staff specialist in clinical research of Moscow Healthcare Department; clinical pharmacologist
Moscow
The authors declare no conflict of interest
Irina B. Bondareva — Dr. Sci. (Bio.), department of General and Clinical Pharmacology
Moscow
The authors declare no conflict of interest
Gleb A. Putsman — graduate student of department of General and Clinical Pharmacology; clinical pharmacologist
Moscow
The authors declare no conflict of interest
Zyryanov S.K., Bondareva I.B., Putsman G.A. Pharmacokinetics and pharmacodynamics of linezolid treatment of bacterial infections in children of different age groups: what do we know today? Kachestvennaya Klinicheskaya Praktika = Good Clinical Practice. 2026;(2):113-129. (In Russ.) https://doi.org/10.37489/2588-0519-GCP-0031. EDN: GRRZAK
НАШИ КНИГИ




Другие журналы
"Издательства ОКИ"


ПАРТНЕРЫ

 Email this article (Login required)
Email the author (Login required)
121357, Moscow, st. Vatutina, 4, building 2, apt. 22
LLC Publishing House OKI
Tel. +7 (926) 568-17-35
e-mail: clinvest@mail.ru


